
Mind map
Endocrine
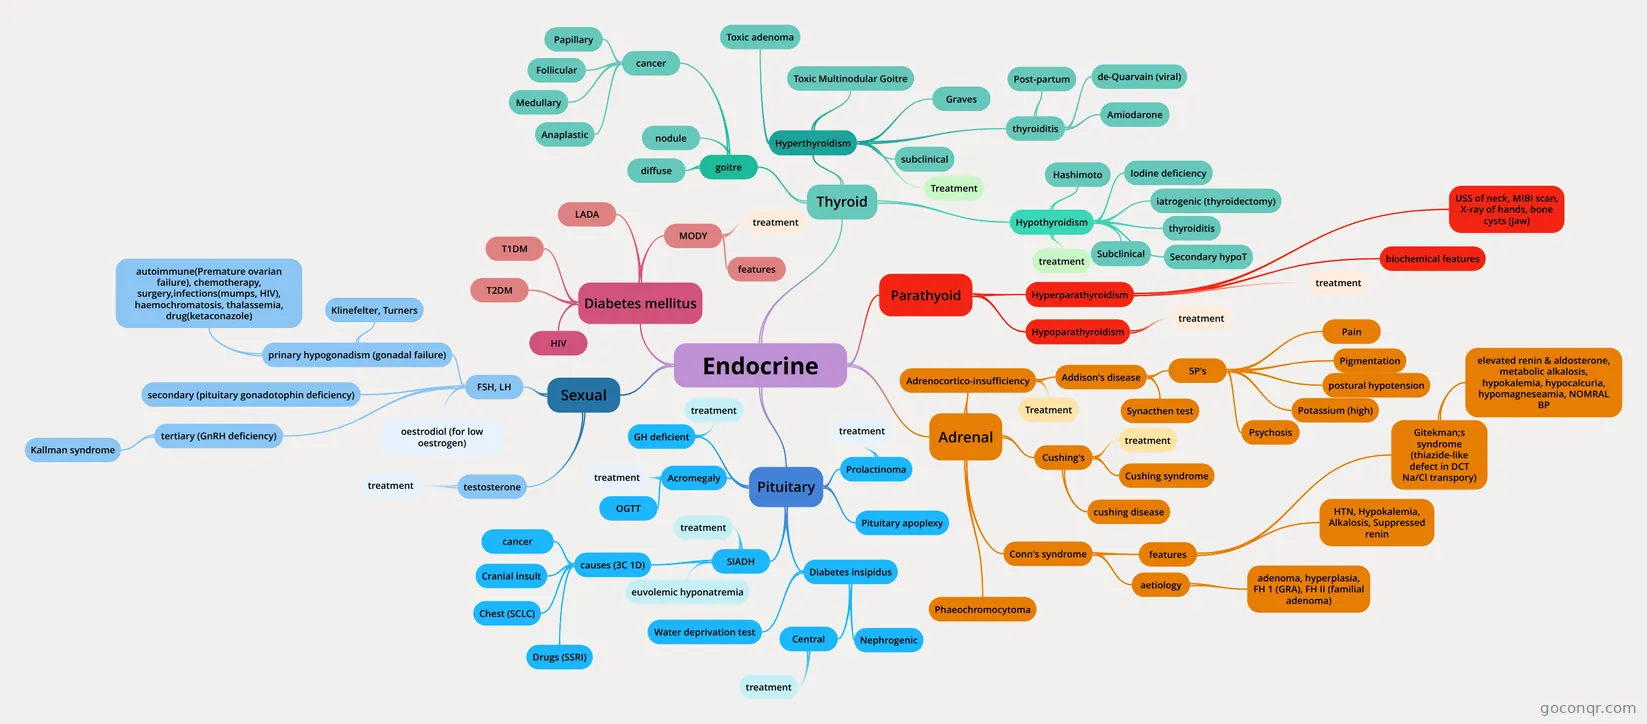
Mind map: Endocrine System Glands and Disorders
Map content
Endocrine
Diabetes mellitus
- T1DM
- Autoab -- glutamic acid decarboxylase (GAD 65) Islet cells Tyrosine phosphatases Zinc transporter *HLA DR4 or DR3
- T2DM
- polygenic not insulin dependent but insulin requiring
- LADA
- Auntoab to B cell antigens Share genetic features with Type 1 or Type 2 *may develop insulin dependence
- MODY
- transcription factor (67%) --HNF Ia (pancreas & islet) --HNF 4a HNF 1b glucokinase (32%)--loss of glucose sensing function
- treatment
- HNF 1a & HNF 4a --low dose sulphonylurea (first line) eg; glicazide, glibenclamide *Insulin can be stopped
- features
- -residual insulin secretion at least 3 years after diagnosis of T1DM -young onset -lack of metabolic syndrome in those presumed T2DM
- HIV
- increased in men on HAART (x4 greater) protease inhibitors & NRTIs; indanavir (blocks insulin mediated GLUT-4 & increases hepatic glucose production)
- T1DM
Thyroid
- Hyperthyroidism
- Low TSH High T3 & T4
- subclinical
- Low TSH Normal T3 &T4
- Graves
- Toxic Multinodular Goitre
- Toxic adenoma
- thyroiditis
- intially presented with hyperthyroidism, and over time becomes hypothyroidism
- Post-partum
- de-Quarvain (viral)
- Amiodarone
- Treatment
- 1. Symptomatic Mx: --beta-blockers 2. Anti-thyroid drugs: PTU (given in pregnancy), Carbimazole (s/e of agranulocytosis) Radioiodine therapy (kill thyroid cells using radioactive substance)3. Surgery
- Hypothyroidism
- High TSH Low T3 & T4
- Subclinical
- High TSH Normal T3 & T4 *Thyroidectomy can mimic such pattern-- when patient who is non-compliance to med
- Secondary hypoT
- Low TSH, T3 and T4
- Hashimoto
- common cause in UK
- Iodine deficiency
- commonest worldwide
- iatrogenic (thyroidectomy)
- recurrent laryngeal nerve -hoarse voice Hypercalcemia - parathyroid gland resected along with the thyroid
- thyroiditis
- tender raised ESR viral / post-partum / drug-induced
- treatment
- Levothyroxine 100-250 micrograms/day caution in elderly, previous IHD, severe hypothyroidism --> can form clots in coronary artery (leading to MI) Thus, start low and go slow (50 micrograms)
- goitre
- diffuse
- nodule
- cancer
- cold nodules (radioisotope scan) -not producing thyroid hormones -undifferentiated cells
- Papillary
- most common better prognosis
- Follicular
- Medullary
- high calcitonin release
- Anaplastic
- poorest prognosis least common
- Hyperthyroidism
Adrenal
- Cushing's
- decrease in muscle mass, increase in fats activation of collagenase--> striae, osteoporosis HTN, DM low K and H+ --> metabolic alkalosis
- Cushing syndrome
- cause: 2/3--adenoma 1/3-- bilateral hyperplasia
- cushing disease
- treatment
- steroidogenesis inhibitors -ketaconazole, metyrapone
- Conn's syndrome
- high BP Low K, thus Low H+ --metabolic alkalosis
- features
- HTN, Hypokalemia, Alkalosis, Suppressed renin
- Gitekman;s syndrome (thiazide-like defect in DCT Na/Cl transpory)
- elevated renin & aldosterone, metabolic alkalosis, hypokalemia, hypocalcuria, hypomagneseamia, NOMRAL BP
- aetiology
- adenoma, hyperplasia, FH 1 (GRA), FH II (familial adenoma)
- Phaeochromocytoma
- Adrenocortico-insufficiency
- primary vs secondary --primary (Addisons) -- Secondary: low ACTH, low cortisol but normal aldosterone (RAAS), no pigmentation
- Addison's disease
- commonest cause in UK -- autoimmune commonest in Msia-- TB High ACTH, low cortisol and aldosterone [all parts of adrenal are destroyed]
- 5P's
- Pain
- Pigmentation
- high ACTH seen in primary adrenocortico- insufficiency
- postural hypotension
- Potassium (high)
- Psychosis
- Synacthen test
- Treatment
- Primary (adrenal insufficiency) -hydrocortisone 5-25mg/day (glucorticoid) -fludrocortisone 0.1-0.2mg/day (mineralocorticoid) Secondary (adrenal insufficiency- pituitary problem) -only hydrocortisone 5-25mg/day *aldosterone release stimulated by RAAS
- Cushing's
Pituitary
- Acromegaly
- OGTT
- treatment
- Somatostatin analogue receptor antagonist; pegvisomant Dopamine receptor agonists; bromocriptine, cabergoline, quinagolide
- Prolactinoma
- treatment
- dopamine receptor agonists -bromocriptine
- treatment
- Pituitary apoplexy
- caused by SAH --reduced blood flow to the pituitary
- Diabetes insipidus
- high sodium levels --can retain water (polyuria) leading to polydipsia [thirst centre in hypothalamus]
- Central
- treatment
- Low ADH-- tablets / nasal inhalations
- treatment
- Nephrogenic
- Water deprivation test
- add Desmopressin (synthetic ADH) to differentiate neurogenic from nephrogenic DI
- SIADH
- low sodium levels --retain too much water by increase action of ADH
- causes (3C 1D)
- cancer
- Cranial insult
- Chest (SCLC)
- Drugs (SSRI)
- SSRI TCA opiates cyclophosphamide NSAIDS PPIs
- euvolemic hyponatremia
- Reduced serum osmolality <275 Increased urine osmolality >100 Increased urine sodium >30 *NO recent use of diuretics No hypotension & hypovolemia, oedema, adrenal/thyroid/renal insufficiency
- treatment
- fluid restriction, democlocycline, tolvaptan
- GH deficient
- treatment
- For children, injections recombinant HGH For adults, controversial use and some undergoing trials
- treatment
- Acromegaly
Sexual
- FSH, LH
- oestrodiol (for low oestrogen)
- prinary hypogonadism (gonadal failure)
- Klinefelter, Turners
- autoimmune(Premature ovarian failure), chemotherapy, surgery,infections(mumps, HIV), haemochromatosis, thalassemia, drug(ketaconazole)
- secondary (pituitary gonadotophin deficiency)
- tertiary (GnRH deficiency)
- Kallman syndrome
- testosterone
- treatment
- Patches, gel, injections *orally inactive use gonadotrophins for infertility
- treatment
- FSH, LH
Parathyoid
- Hyperparathyroidism
- benign solitary parathyroid adenoma (85%) '4-gland' parathyroid hyperplasia (15%) parathyroid carcinoma <1%
- treatment
- surgery (definitive; 1st line) if surgery fail, cinacalcet (receptor antagonist)
- biochemical features
- increased serum calcium increased parathyroid hormone Raised urine calcium Low serum phosphate (negative feedback) Mild metabolic acidosis
- USS of neck, MIBI scan, X-ray of hands, bone cysts (jaw)
- Hypoparathyroidism
- treatment
- PTH injections (expensive) High dose vit D (monitor urine calcium)
- treatment
- Hyperparathyroidism
Information
- Description
- Medicine Mind Map on Endocrine, created by Crystal Wong on 26/11/2018.
- Created by
- Crystal Wong
- Views
- 0
- Rating