9924449
Description


| Question | Answer |
| Hyperplasia | - increase in stress leads to increase in organ size 2/2 increased number of cells - involves production of new cells from stem cells |
| Hypertrophy | - increase in stress leads to increase in organ size 2/2 increase in cell size - involves gene activation, protein synthesis, and organelle production |
| Three types of permanent tissue: | - cardiac myocytes - skeletal muscle - nerve tissue (only undergo hypertrophy) |
| Pathologic hyperplasia... | can progress to dysplasia and cancer (except for BPH) |
| Atrophy | decrease in stress leads to decreased organ size 2/2 decrease in cell size (via ubiquitin-proteosome degradation of cytoskeleton and autophagy of cellular components) OR number (via apoptosis) |
| Metaplasia | - stress on organ changes leading to change in cell type to better handle new stress - occurs via re-programming of stem cells - REVERSIBLE - can progress to dysplasia and cancer (except: apocrine metaplasia in fibrocystic change in breast) |
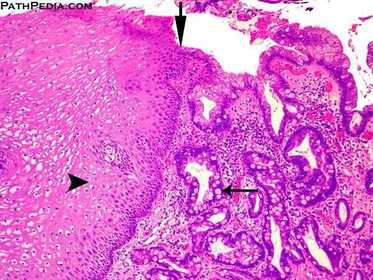
| Barrett’s metaplasia of esophagus is defined as replacement of the normal squamous epithelium of distal esophagus by metaplastic glandular epithelium containing intestinal-type goblet cells. Note the squamous epithelium on the left (arrowhead) is continuous with the metaplastic epithelium containing goblet cells (long thin arrow) on the right. The transition is shown by downward arrow on the top | |
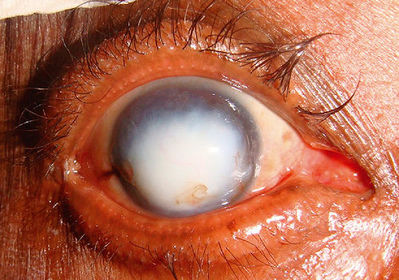
| Keratomalacia: vit A deficiency --> metaplasia of thin squamous lining of conjunctiva into stratified keratinized squamous epithelium | |
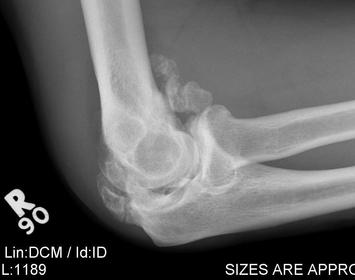
| Myositis ossificans: metaplasia of mesenchymal tissue (skeletal muscle) to bone during healing after trauma | |
| Dysplasia | - disordered cellular growth - proliferation of precancerous cells arising from longstanding pathologic hyperplasia or metaplasia - REVERSIBLE |
| Aplasia | failure of cell production during embryogenesis |
| Hypoplasia | decrease in cell production during embryogensis (ex: streak ovary in Turner syndrome) |
| Injury occurs... | when stress exceeds cell's ability to adapt (depends on type of stress, severity, and type of cell affected) |
| Hypoxia | low oxygen delivery to tissues (low O2 --> low ATP 2/2 impaired oxidative phosphorylation --> cellular injury) |
| Causes of hypoxia: | - ischemia - hypoxemia - decreased O2-carrying capacity of blood |
| Ischemia | - decreased blood flow through an organ - 3 mechanisms: blocked artery, blocked vein, or shock |
| Hypoxemia | - low partial pressure of O2 in blood (SaO2 < 90%) - FiO2 --> PAO2 (inverse to PACO2) -- diffusion barrier (ex: thickened in interstitial fibrosis)--> PaO2 --> SaO2 |
| Decreased O2-carrying capacity of blood | - 2/2 Hb loss or dysfunction - ex: anemia, CO poisoning, methemoglobinemia |
| CO Poisoning | - Early: headache - Late: coma, death - PE: cherry-red skin |
| Methemoglobinemia | - oxidants and newborns (immature reduction machinery) - cyanosis w/chocolate-colored blood - IV methylene blue reduces back to Fe2+ |
| Low ATP disrupts: | - Na+/K+ pump --> cell swelling 2/2 Na+ accumulation - Ca++ pump --> NZ activation - aerobic glycolysis --> lactic acidosis (low pH --> DNA and protein precipitation) |
| Reversible Injury | CELL SWELLING (loss of villi, membrane blebbing, swelling of RER --> decrease in protein synthesis) |
| Irreversible Injury | MEMBRANE DAMAGE (cell membrane --> NZ leak, influx Ca++, lysosome membrane --> autophagy, mitochondria membrane --> decrease ATP, leak cytochrome C --> apoptosis) |
| Free radical | chemical species with unpaired electron in outer orbit |
| Physiologic generation of free radicals: | occurs during oxidative phosphorylation: partial reduction of O2 --> O2- (1), H2O2 (2), OH- (3) --> H2O (4) |
| Pathologic generation of free radicals: | - metals (i.e. copper + iron) - ionizing radiation (OH-) - inflammation (oxidative burst; O2 --> O2- via NADPH oxidase) - drugs and chemicals (e.g. acetaminophen) |
| What do free radicals do? | - peroxidation of lipids - oxidation of DNA and proteins |
| Elimination/prevention of free radicals: | - NZs - antioxidants (SOD - O2-, catalase - H2O2 [vs MPO --> HOCl], glutathione peroxidase - OH-) - metal carrier proteins |
| CCl4 | - drycleaning industry - P450 in liver --> CCl3- --> protein oxidation --> decreased apolipoproteins --> decreased fat transport --> fatty liver disease |
| Reperfusion Injury | classic vignette: cont. rise in cardiac NZs after MI intervention |
| Saponification | fat damage --> FAs released by trauma or lipase --> combine w/Ca++ --> chalky white deposits |
| Causes of fibrinoid necrosis: | - malignant HTN - vasculitis |
| Amyloid | misfolded, B-pleated protein *stains Congo Red w/apple-green birefringence under polarized light |
| Commonly affected organs in amyloidosis: | - Kidneys --> nephrotic syndrome - Heart --> restrictive cardiomyopathy |
Want to create your own Flashcards for free with GoConqr? Learn more.