
Mind map
Upper GI bleed
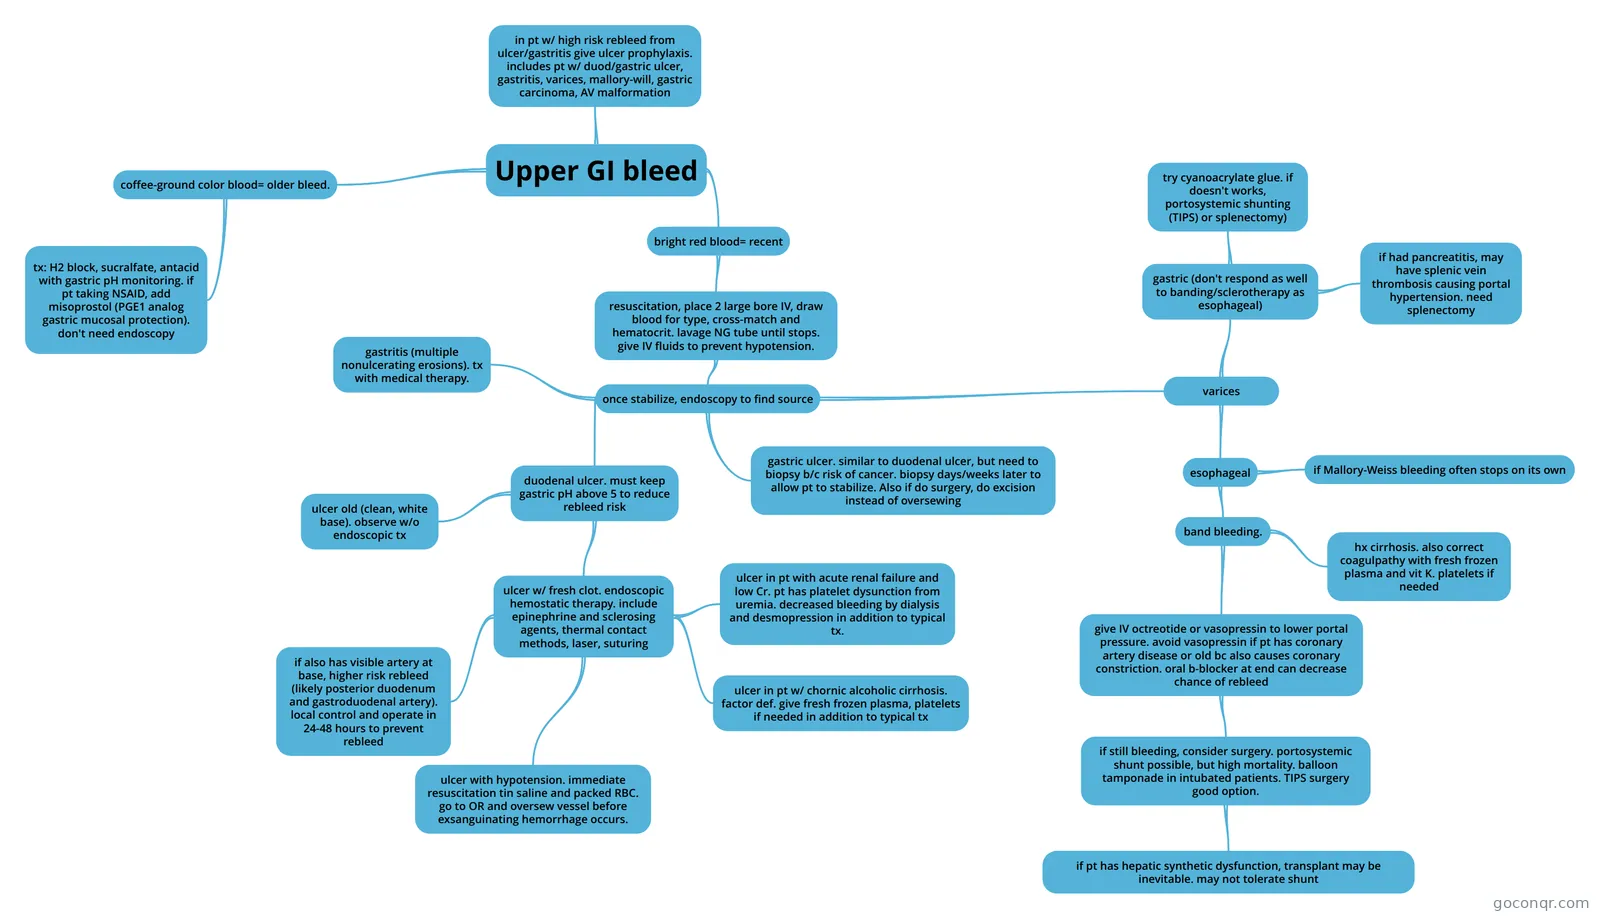
Mind map: Upper GI bleed
Map content
Upper GI bleed
coffee-ground color blood= older bleed.
- tx: H2 block, sucralfate, antacid with gastric pH monitoring. if pt taking NSAID, add misoprostol (PGE1 analog gastric mucosal protection). don't need endoscopy
in pt w/ high risk rebleed from ulcer/gastritis give ulcer prophylaxis. includes pt w/ duod/gastric ulcer, gastritis, varices, mallory-will, gastric carcinoma, AV malformation
bright red blood= recent
- resuscitation, place 2 large bore IV, draw blood for type, cross-match and hematocrit. lavage NG tube until stops. give IV fluids to prevent hypotension.
- once stabilize, endoscopy to find source
- duodenal ulcer. must keep gastric pH above 5 to reduce rebleed risk
- ulcer old (clean, white base). observe w/o endoscopic tx
- ulcer w/ fresh clot. endoscopic hemostatic therapy. include epinephrine and sclerosing agents, thermal contact methods, laser, suturing
- if also has visible artery at base, higher risk rebleed (likely posterior duodenum and gastroduodenal artery). local control and operate in 24-48 hours to prevent rebleed
- ulcer with hypotension. immediate resuscitation tin saline and packed RBC. go to OR and oversew vessel before exsanguinating hemorrhage occurs.
- ulcer in pt with acute renal failure and low Cr. pt has platelet dysunction from uremia. decreased bleeding by dialysis and desmopression in addition to typical tx.
- ulcer in pt w/ chornic alcoholic cirrhosis. factor def. give fresh frozen plasma, platelets if needed in addition to typical tx
- gastric ulcer. similar to duodenal ulcer, but need to biopsy b/c risk of cancer. biopsy days/weeks later to allow pt to stabilize. Also if do surgery, do excision instead of oversewing
- gastritis (multiple nonulcerating erosions). tx with medical therapy.
- varices
- esophageal
- band bleeding.
- hx cirrhosis. also correct coagulpathy with fresh frozen plasma and vit K. platelets if needed
- give IV octreotide or vasopressin to lower portal pressure. avoid vasopressin if pt has coronary artery disease or old bc also causes coronary constriction. oral b-blocker at end can decrease chance of rebleed
- if still bleeding, consider surgery. portosystemic shunt possible, but high mortality. balloon tamponade in intubated patients. TIPS surgery good option.
- if pt has hepatic synthetic dysfunction, transplant may be inevitable. may not tolerate shunt
- if still bleeding, consider surgery. portosystemic shunt possible, but high mortality. balloon tamponade in intubated patients. TIPS surgery good option.
- if Mallory-Weiss bleeding often stops on its own
- band bleeding.
- gastric (don't respond as well to banding/sclerotherapy as esophageal)
- try cyanoacrylate glue. if doesn't works, portosystemic shunting (TIPS) or splenectomy)
- if had pancreatitis, may have splenic vein thrombosis causing portal hypertension. need splenectomy
- esophageal
- duodenal ulcer. must keep gastric pH above 5 to reduce rebleed risk
- once stabilize, endoscopy to find source
- resuscitation, place 2 large bore IV, draw blood for type, cross-match and hematocrit. lavage NG tube until stops. give IV fluids to prevent hypotension.
Information
- Description
- Surgery (Upper GI Disorders) Mind Map on Upper GI bleed, created by mdeol2017 on 26/08/2015.
- Created by
- mdeol2017
- Views
- 2
- Rating
More on Gastrointestinal Bleeding